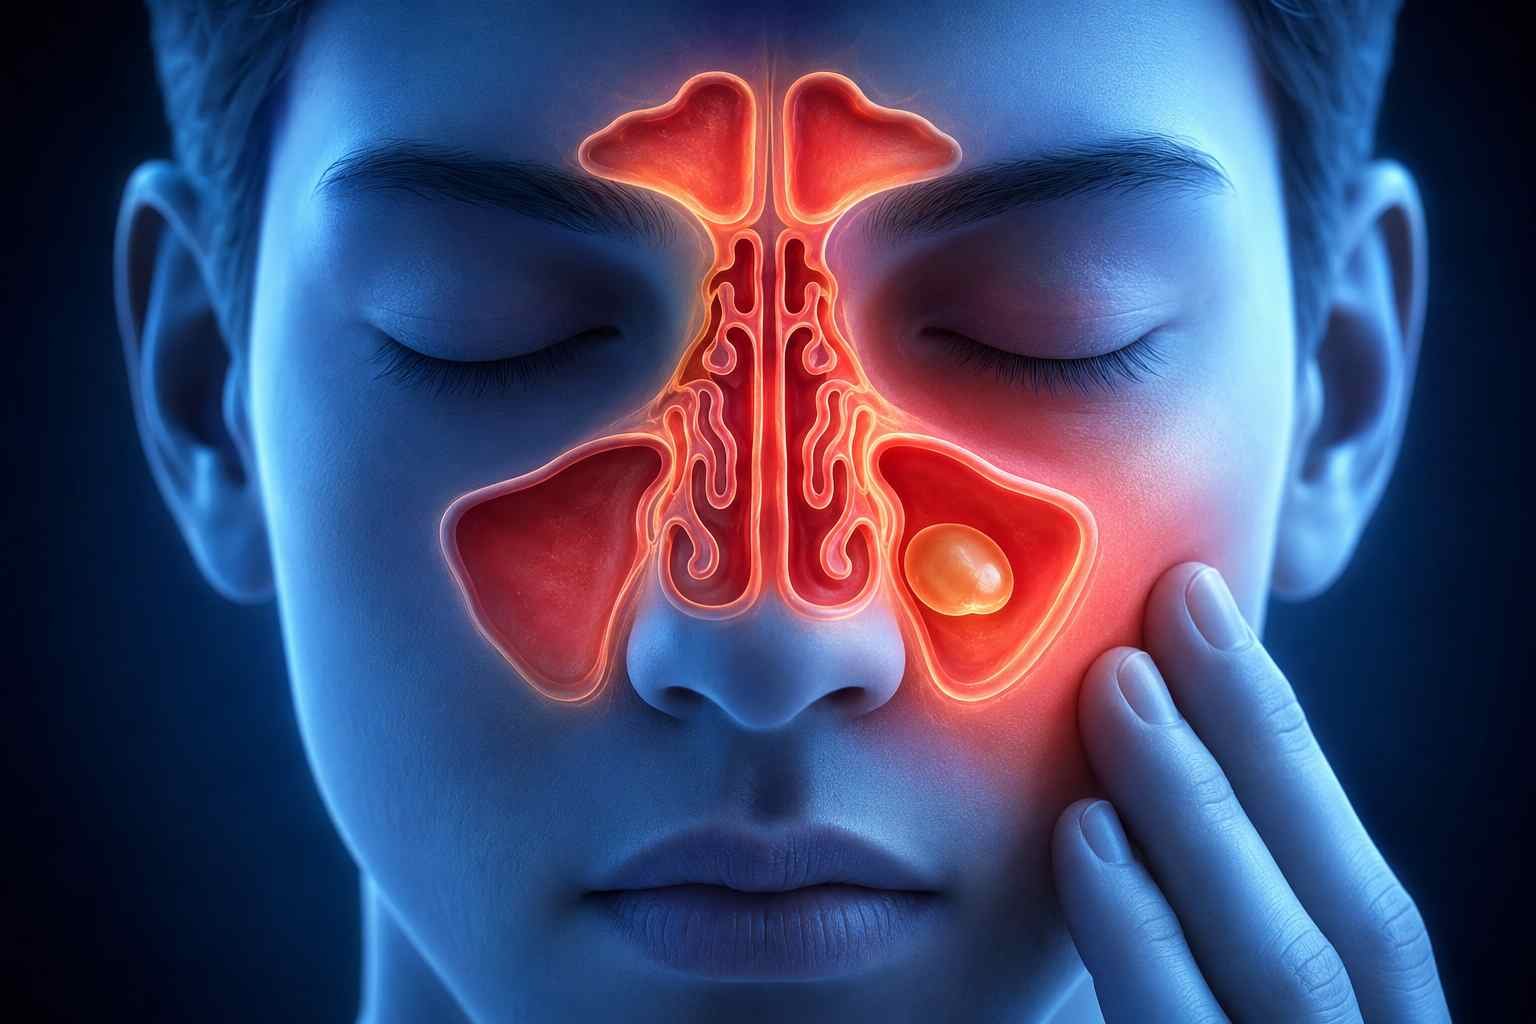
What Are the Symptoms of a Cyst in the Sinus?
The majority of sinus cysts (like mucous retention cysts) are tiny, benign, and asymptomatic. When huge cysts or mucoceles obstruct drainage routes, they might result in localised facial pressure or discomfort, boring headaches, a congested nose, tooth sensitivity, or reoccurring sinus infections.
By Dr. Sagar Rajkuwar, ENT Specialist, Nashik, Maharashtra, India
🌐 www.entspecialistinnashik.com
Table of Contents
- Introduction
- What Is a Sinus Cyst?
- What exactly is a maxillary sinus retention cyst?
- Symptoms of Sinus Cyst Are Common.
- When Are Sinus Cysts Asymptomatic?
- Can a headache or facial pain be brought on by a sinus cyst?
- Risk Factors and Causes
- Sinus Cyst vs Nasal Polyp vs Mucocele
- Dental issues and a sinus cyst
- Is it possible for a sinus cyst to be dangerous?
- Diagnosis
- When Is Treatment for a Sinus Cyst Necessary?
- Medical Care
- Surgical Sinus Endoscopy
- Postoperative Recovery Following Endoscopic Sinus Surgery
- Is it possible for a sinus cyst to disappear on its own?
- Is It Possible for Sinus Cysts to Reappear?
- Preventing Sinus Issues in the Future
- When Should I Consult an ENT Specialist?
- FAQs
- Key Takeaways
- Conclusion
- 📞 ENT Consultation
- Medical Disclaimer
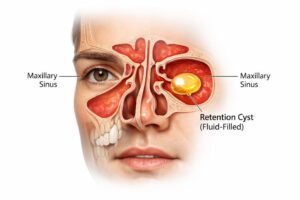
A Complete Guide to Maxillary Sinus Retention Cysts
1.Introduction
A cyst in the sinus, most commonly a maxillary sinus retention cyst, is a benign, fluid-filled sac that forms inside the sinus cavity. These cysts are often discovered incidentally during dental X-rays or CT scans done for other reasons. In many cases, they cause no symptoms at all. However, when they grow larger or coexist with sinus inflammation, they may lead to discomfort and chronic sinus complaints.
Understanding the symptoms, causes, diagnosis, and treatment options for sinus cysts is essential for timely care and long-term relief. This article explains everything you need to know about sinus retention cysts in clear, patient-friendly language.
📊 How common are sinus cysts? (Updated evidence 2026) Based on multiple radiographic surveys, maxillary mucous retention cysts are detected on roughly 1.6% to 10% of imaging studies, depending on the imaging modality and population. A large Turkish panoramic-radiograph study of 9,659 patients reported a 1.6% frequency, while cone-beam CT studies — which are more sensitive — show higher detection rates. A central Brazilian population study of 631 panoramic X-rays found 6.89% suggestive of mucous retention cysts, and a Peruvian study of adults found a 7.6% prevalence. These numbers highlight that the condition is more common than most patients think, yet in the overwhelming majority of cases it never causes symptoms and never needs treatment.
2. What is a sinus cyst?
A benign, fluid-filled or mucus-filled lesion connected to the sinus lining is known as a sinus cyst.
A maxillary sinus mucous retention cyst, which is commonly brought on by the obstruction of a little mucus gland duct in the sinus lining, is one of the most frequent discoveries.
These cysts are usually:
- Benign
- non-malignant
- frequently discovered by accident
- Generally change slowly
- Often without symptoms
A literature study revealed that maxillary mucous retention cysts are harmless and mostly asymptomatic.
🧪 The two main types of true sinus cysts you should know:
- Mucous (serous) retention cyst — forms when a submucosal mucus-gland duct becomes blocked and fluid collects beneath the sinus lining. These are by far the most common type and typically appear as a smooth, dome-shaped shadow on imaging. They do not expand the bony sinus walls.
- Mucocele — a mucus-filled, slowly expanding lesion that forms when the whole sinus outlet is obstructed. Unlike a simple retention cyst, a mucocele can enlarge the sinus itself, thin or erode the surrounding bone, and press on the eye or brain. Mucoceles most commonly affect the frontal sinus (around 60% of cases), followed by the ethmoid; maxillary sinus mucoceles make up less than 5–10%.
Other lesions sometimes misread as “sinus cysts” include antrochoanal polyps (soft-tissue lesions arising from the maxillary sinus), odontogenic cysts (such as radicular or dentigerous cysts arising from the teeth), and rarer sinus tumours. This is why a careful imaging review and, if needed, an ENT and dental evaluation matter — not every “cyst” seen on a scan is the same thing or carries the same meaning.
3. What exactly is a maxillary sinus retention cyst?
The cheekbones hide the maxillary sinuses.
When the duct of a mucus gland is blocked, a retention cyst of the maxillary sinus can form. A rounded, dome-shaped lesion is created when secretions gather under the lining of the sinuses.
These cysts are frequently found along the walls or floor of the maxillary sinus.
Key point
A retention cyst shouldn’t be immediately thought of as being the same as:
- A polyp in the nose
- A mucocele is a cyst in the mouth.
- An odontogenic cyst
- A tumor of the sinus
- Chronic sinusitis
Therefore, a precise interpretation of the picture is essential.
📍 Where exactly do these cysts sit? (new anatomical insight) Multiple radiographic cohort studies show the vast majority — around 70–75% of maxillary retention cysts — form on the floor of the maxillary sinus (the part sitting directly above the roots of the upper molar and premolar teeth). The remainder are found along the lateral and medial walls. This floor-dominant distribution is clinically important: because the floor of the maxillary sinus is only a thin layer of bone away from the upper back-tooth roots, dental disease and dental procedures can both trigger and mimic a sinus cyst. The classic dome-shaped, well-defined, water-density (“mucosal-density”) lesion on CT is the usual appearance of a benign retention cyst.
4. Symptoms of Sinus Cyst Are Common.
Numerous individuals exhibit no symptoms whatsoever.
Possible symptoms are:
1. Pain or pressure in the face
Certain patients may have:
- cheek pressure
- Under the eye, there is discomfort.
- Force to the top jaw
- Heavy Face
However, face pain does not always indicate that the cyst is to blame.
Clinical tip: True sinus-cyst facial pressure is usually dull, one-sided, and worse when bending forward. Sharp, throbbing, light-sensitive or nausea-associated pain is more typical of migraine than of a sinus cyst, even when a cyst happens to show up on the scan.
2. Headaches
Particularly when other sinus inflammation is present, some patients may complain of headaches or pressure in the face.
Migraine and other headache disorders can produce similar symptoms, thus a sinus cyst shouldn’t be immediately considered to be the cause of a headache.
Important update: Peer-reviewed reviews of maxillary mucous retention cysts have repeatedly found no consistent link between the simple presence of a retention cyst and chronic headache. Studies in which patients with incidentally found cysts were followed over time show that most people do not develop new headaches even as the cyst persists. If a headache is being blamed on a cyst, an ENT specialist will usually look for other possibilities — migraine, tension-type headache, chronic rhinosinusitis, temporomandibular joint (TMJ) dysfunction and dental pathology — before deciding the cyst is responsible.
3. Congestion of the nose
When there is concomitant nasal or sinus inflammation or obstruction, nasal blockage may happen.
If one side of the nose has been persistently blocked for weeks — especially if it is accompanied by foul-smelling discharge, bleeding, or facial swelling — the blockage is usually driven by something other than a small retention cyst, and an ENT evaluation to rule out unilateral sinus disease is strongly recommended.
4. Drip Postnasally
A cough is caused by mucus seeping down into the throat.
- Irritation of the throat
- Frequent throat clearing
- Coughing
Postnasal drip related to true sinus disease is often worse at night and on waking because mucus pools in the nasopharynx while lying down. Simple measures that are supported by evidence — such as nightly saline nasal irrigation and head-elevation while sleeping — frequently reduce this symptom even before any specific cyst treatment is considered.
5. Persistent Sinus Issues
Patients with comorbid chronic rhinosinusitis may suffer:
- Pressure on the face
- Blockage in the nose
- Discharge from the nose
- Less odor
When chronic rhinosinusitis coexists with a retention cyst, treating the underlying inflammation — with saline rinses, intranasal corticosteroid sprays, allergy control, and in selected cases antibiotics or surgery — often improves the symptoms, even though the cyst itself may remain visible on follow-up scans.
6. Lack of Olfactory Perception
Nasal inflammation, polyps, or chronic rhinosinusitis are more frequently linked to a diminished sense of smell than an isolated small retention cyst.
If smell loss is sudden or complete, additional causes such as viral infection (including post-COVID anosmia), nasal polyps, head injury or neurological conditions need to be considered. A standalone retention cyst almost never fully destroys the sense of smell.
7. Upper Tooth or Jaw Pain
Dental illness can cause symptoms similar to sinus disease since the roots of the top back teeth are near to the maxillary sinus.
Because the roots of the second premolar and first/second molars often lie within 1–2 mm of the sinus floor — and sometimes project directly into the sinus — pulp infection, periapical abscess, or periodontal disease can produce facial pressure that feels exactly like a sinus problem. According to published reviews, up to 30–50% of all maxillary sinus infections, and as many as 75% of one-sided maxillary sinus infections, originate from a dental source. A dental examination is therefore essential whenever upper-tooth pain and sinus symptoms occur together.
🧭 Symptom infographic — “Sinus cyst vs the real culprit”
| Symptom | Likely from a sinus cyst? | More likely cause |
|---|---|---|
| Dull one-sided cheek pressure | Possibly | Chronic sinusitis, dental infection |
| Throbbing headache + nausea + light sensitivity | Unlikely | Migraine |
| Blocked nose on one side only, foul discharge | Possibly, if obstructing drainage | Odontogenic sinusitis, fungal ball, polyp |
| Upper molar pain | Rarely primary | Dental caries, periapical abscess |
| Progressive eye swelling or vision change | No — think mucocele / tumour | Sinus mucocele, orbital complication |
5. When Are Sinus Cysts Asymptomatic?
This is one of the most critical portions for patients.
For years, a sinus retention cyst may remain absolutely quiet.
Studies of asymptomatic groups have discovered that mucous retention cysts are accidentally seen on imaging, suggesting that their existence does not always indicate active sinus illness.
When a cyst is clinically insignificant, it is more probable that it will:
- accidentally discovered
- Sinus drainage is not blocked.
- is not associated with serious inflammation.
- Causes no symptoms that correspond.
In such cases, observation could be sufficient.
What the imaging data actually shows: General-population imaging surveys in asymptomatic volunteers consistently find that incidental mucous retention cysts and mucosal thickening of the sinuses are common findings in people with no complaints at all. This is why specialists are cautious about automatically connecting a scan finding with the patient’s symptoms. In practice, if a cyst is small, located away from the natural ostium (the sinus’s main drainage opening), and the patient is well, the standard approach is reassurance and watchful waiting rather than treatment.
6. Can a headache or facial pain be brought on by a sinus cyst?
This is a typical question.
Even though a big or advantageously located lesion can occasionally aggravate symptoms, the discovery of a sinus retention cyst by itself does not establish the origin of headache or facial pain.
There was no clear link between sinonasal symptoms and mucous retention cysts of the maxillary sinus, according to an assessment of these cysts.
As a result, if a CT scan reveals a sinus cyst and the patient experiences severe headache, the ENT expert should take into account additional factors such as:
- headache
- Headache with tension
- Long-term rhinosinusitis
- Illness of the teeth
- disorders of the temporomandibular joint
- additional neurological causes
How ENT doctors tell the difference: A pragmatic test is to treat the possible co-existing conditions — allergic rhinitis, chronic rhinosinusitis, migraine or tooth disease — and reassess. If the headache resolves while the cyst is still present on imaging, the cyst was almost certainly a bystander, not the cause. Conversely, if symptoms persist despite good control of other causes, a localized obstructive effect of the cyst (especially a large one near the ostiomeatal complex) can be reconsidered.
7. Risk Factors and Causes
Retention cysts and inflammation of the sinus mucosa might be caused by a number of factors, including:
Inflammation caused by an allergic reaction
The lining of the nose and sinuses might become inflamed as a result of allergic rhinitis.
Sinus inflammation that recurs
Normal mucous drainage may be impaired by chronic inflammation.
Obstruction of the duct of a mucus gland
A retention cyst’s basic mechanism is this one.
dental conditions
Particularly when sinus illness appears only on one side, upper tooth infections should be taken into account since they can have an impact on the maxillary sinus.
It’s crucial to understand that a straightforward maxillary sinus retention cyst and a dental infection are not the same thing.
➕ Additional modern risk factors supported by the literature:
- Male sex — several large panoramic-radiograph studies have found a higher prevalence of maxillary retention cysts in men.
- Age 30–40 — peak detection in both Turkish and Brazilian cohorts, although cysts occur across all age groups.
- Smoking — tobacco smoke is a well-established cause of mucociliary dysfunction, impaired drainage and chronic sinus inflammation (WHO, CDC).
- Environmental air pollution and occupational dust exposure — chronic irritant exposure drives mucosal inflammation.
- Prior dental procedures — root canals, upper molar extractions, implants and sinus-floor augmentation can all disturb the sinus lining.
- Climate and humidity — some studies suggest seasonal variation in cyst detection, possibly reflecting changes in allergen exposure and mucosal activity.
- Underlying anatomy — a deviated septum or narrow ostiomeatal complex can impair drainage and favour cyst and mucocele formation.
Despite these associations, in a large proportion of patients no clear trigger can be identified, and the cyst simply reflects a blocked mucus gland without any sinister cause.
8. Sinus Cyst vs Nasal Polyp vs Mucocele
| Feature | Retention Cyst | Nasal Polyp | Mucocele |
|---|---|---|---|
| Basic nature | Mucus/fluid-containing lesion | Inflamed soft tissue | Expanded mucus-filled sinus |
| Typical cause | Blocked mucus gland duct | Chronic inflammation | Blocked sinus drainage |
| Usually benign? | Yes | Generally benign | Generally benign |
| Can be incidental? | Frequently | Sometimes | Less commonly |
| Treatment | Often observation | Medical treatment ± surgery | Usually requires specialist management |
| Can expand sinus walls? | Usually no | Usually no | May cause expansion |
These conditions should not be treated as interchangeable.
Why mucoceles are a bigger deal than retention cysts: A simple retention cyst stays confined to the mucosal lining. A mucocele, by contrast, slowly expands the whole sinus and can press on neighbouring structures. According to a recent clinical series of paranasal sinus mucoceles, patients commonly presented with proptosis (bulging eye) in roughly 32% of cases and blurred vision in about 26%, along with facial pain and swelling. Frontal and ethmoid mucoceles can push into the orbit; sphenoid mucoceles sit near the optic nerve and brainstem; large maxillary mucoceles can cause cheek swelling and even displace the eye. These behaviours never occur with a small retention cyst and are the main reason to distinguish the two accurately on imaging.
9. Dental issues and a sinus cyst
Especially important is the relationship between the upper teeth and the maxillary sinus.
Odontogenic maxillary sinusitis can result from a variety of dental procedures, including dental implants, tooth extraction, root canal issues, periodontal disease, and dental infections.
Due to its frequent unilateral nature, odontogenic sinusitis may go undiagnosed if the dental cause is not specifically assessed.
At what time should dental sickness be suspected?
When there is a: to think about a dental assessment.
- Unilateral maxillary sinus disease
- Pain in the upper tooth
- Current Dental Care
- Drainage that tastes awful or smells bad
- Periapical dental disease seen on CT
- Unilateral sinusitis that keeps coming back
Collaboration between dental and ENT experts may be required in certain situations.
📊 How often is a one-sided sinus problem actually dental in origin? Published reviews now estimate that approximately 30–50% of all maxillary sinusitis cases are of dental (odontogenic) origin, and in up to 75% of unilateral maxillary sinus cases a dental cause is responsible. A cone-beam CT (CBCT) study of 96 patients with suspected maxillary sinusitis found an odontogenic cause in 60% of cases. The clinical message is simple: any one-sided maxillary sinus finding — including what looks like a “cyst” — should prompt at least a dental review before major sinus surgery is considered. Treating the dental source alone (root canal, extraction or cyst enucleation) often resolves the sinus disease without the need for separate sinus surgery.
10. Is it possible for a sinus cyst to be dangerous?
Normally, a common maxillary sinus retention cyst is not dangerous and is not seen as a precursor to cancer.
However, not all lesions that appear cystic on a scan are necessarily just simple retention cysts.
Further assessment is necessary in cases of uncertainty regarding the diagnosis, major expansion, anomalous symptoms, bleeding, substantial unilateral disease, bone destruction, or atypical imaging results.
Unilateral sinus disease has a wide differential diagnosis, and CT, nasal endoscopy, and in some situations, MRI may be necessary, depending on the results.
🚨 Red flags that should never be ignored (based on international ENT guidance):
- Unexplained bleeding from the nose or sinuses, especially one-sided
- Progressive one-sided facial swelling or numbness over the cheek
- Loosening of upper teeth without obvious dental cause
- Double vision, bulging eye, loss of vision or pupil changes
- Severe one-sided headache that is new, progressive, or associated with neurological symptoms
- Visible erosion of the sinus wall, orbital floor or skull base on imaging
- A rapidly enlarging lesion on follow-up scans
These features are not typical of a simple retention cyst and should prompt urgent ENT review and, when needed, biopsy.
11. Diagnosis
Several procedures are typically used to make a diagnosis.
Medical history
The ENT specialist might inquire about:
- Discomfort in the face
- Obstruction of the nose
- Migraines
- Persistent sinus infections
- Symptoms of the teeth
- Allergies
- Prior sinus surgery
- Nasal Endoscopy
The nasal cavity and sinus outflow regions can be examined using a tiny flexible or rigid endoscope.
Sinus CT scan
A CT scan is capable of demonstrating:
- The place
- Dimension
- Figure
- Related Mucosal Disease
- Obstruction in the route of drainage
- proximity to the nearest teeth
CT is especially helpful when assessing chronic or one-sided sinus disease.
🆕 The role of cone-beam CT (CBCT): Over the last decade, cone-beam CT has become a key imaging tool. CBCT delivers a much lower radiation dose than conventional multi-slice CT, provides high-contrast resolution of bone, teeth and sinus floor, and allows dentists and ENT specialists to clearly see the relationship between the sinus and tooth roots. Studies show CBCT detects odontogenic sinus pathology that panoramic X-rays miss, and current recommendations encourage its use when the clinical picture is one-sided or does not improve with treatment.
MRI
For every basic retention cyst, an MRI is not always necessary.
When the diagnosis is in doubt or imaging indicates a different kind of soft-tissue lesion, it may be taken into consideration.
MRI is especially useful when the ENT specialist needs to rule out a tumour, a fungal ball, or extension of disease into the eye or brain — scenarios where soft-tissue detail is more important than bony anatomy.
12. When Is Treatment for a Sinus Cyst Necessary?
Treatment is not required for all sinus cysts.
When the cyst:
was found by accident
Produces no significant symptoms
It doesn’t hinder the drainage.
Has common benign imaging findings
Treatment may be taken into account if there is strong proof that the lesion is leading to clinically significant symptoms or obstruction.
The need for surgery should not be automatically decided solely on the size of the cyst.
According to a potential randomized study on symptomatic maxillary retention cysts, restoring sinus ventilation and drainage, as opposed to only excising the cyst itself, is essential for treatment outcomes.
Evidence-based decision rule for treatment: The modern ENT consensus is that surgery for a maxillary retention cyst should only be considered when all of the following apply:
- The patient has persistent, bothersome symptoms that are affecting quality of life.
- Other causes — allergic rhinitis, chronic rhinosinusitis, dental disease, migraine, TMJ dysfunction — have been reasonably excluded or treated.
- Imaging shows the cyst is actually obstructing drainage or sits in a clinically meaningful position.
- Medical management with saline rinses and intranasal corticosteroids has failed over a reasonable period.
In the absence of these criteria, observation remains the preferred management, even for cysts that look large on a scan.
13. Medical Care
Retention cysts are not directly treated by medical means.
Treatment may be effective if there is concomitant allergy or inflammation.
An ENT expert may advise the following, depending on the diagnosis:
- Nasal irrigation with salt water
- Corticosteroids given intranasally
- treatment for allergies
- Management of bacterial sinusitis when properly diagnosed
- Dental treatment with a discovered dental source
Without the right medical advise, decongestant medications should not be used on a regular basis or for extended amounts of time.
What the evidence says about these treatments:
- Saline nasal irrigation: High-volume saline irrigation (such as a sinus rinse bottle or neti pot) is now a first-line, guideline-recommended treatment for chronic sinus symptoms. A large UK primary-care randomised trial in over 600 adults found that patients using saline irrigation spent fewer days unwell with sinus symptoms at six months (an average of 4 days vs 7 days without irrigation). The Royal College of Surgeons/ENT UK commissioning guidance and multiple international guidelines recommend saline irrigation and nasal corticosteroid spray together as the standard medical approach. Use only bottled, distilled or previously boiled and cooled water for irrigation — tap water carries a small but real risk of serious infection.
- Intranasal corticosteroid sprays (e.g. fluticasone, mometasone, budesonide): Shrink mucosal inflammation, reduce congestion and improve drainage. They are safe for long-term use at the standard dose and typically take 2–4 weeks of consistent daily use to reach their full effect.
- Antihistamines and allergy control: Helpful when allergic rhinitis is driving the inflammation, especially during pollen seasons.
- Antibiotics: Reserved for proven bacterial sinusitis. NICE guidance notes that even bacterial sinusitis is usually self-limiting and does not routinely need antibiotics; they are considered only if symptoms persist beyond 10 days or are severe with high fever and purulent discharge.
- Dental treatment: When an odontogenic source is identified, treating the tooth (root canal, extraction, or cyst removal) often clears the sinus disease without needing sinus surgery.
⚠️ A word of caution on oral decongestants and nasal decongestant sprays: Over-the-counter decongestant sprays (such as oxymetazoline or xylometazoline) should not be used for more than 3–5 days in a row, because they cause rebound congestion (rhinitis medicamentosa). Oral decongestants should also be avoided in people with high blood pressure, heart disease, glaucoma or prostate enlargement without medical advice.
14. Surgical Sinus Endoscopy
For suitable maxillary sinus disease, an endoscopic endonasal method is often employed when surgery is truly indicated.
The objective can be to:
- Reestablish sinus ventilation
- Drainage should be improved.
- Treat impediment illness.
- Treat related persistent sinus disease
- If necessary, remove or get to a problematic lesion.
When surgical treatment is required, endonasal endoscopic procedures are typically the preferred method, according to a evaluation of maxillary sinus mucous retention cysts.
Nevertheless, a tiny retention cyst seen on a CT scan shouldn’t be reason enough to advise surgery.
What functional endoscopic sinus surgery (FESS) actually involves: FESS is a minimally invasive procedure usually performed under general anaesthesia through the nostrils, with no external cuts on the face. Using a thin endoscope and precise instruments (and increasingly, image-guided navigation), the surgeon widens the natural sinus openings, treats blocking disease and, when needed, marsupialises or removes the cyst or mucocele. Most people go home the same day or the day after surgery. Serious complications are rare: large national data sets suggest that significant eye complications occur in roughly 1 in several thousand FESS procedures, and cerebrospinal-fluid leaks are also rare but well-recognised potential risks. These risks are substantially reduced when the surgery is performed by an experienced rhinologist. For a true mucocele — unlike a simple retention cyst — surgery is almost always required because mucoceles continue to expand and can threaten the eye or brain if left alone.
15. Postoperative Recovery Following Endoscopic Sinus Surgery
Depending on the specific operation done and if extra sinus surgery is necessary, recovery times might vary.
The following might be experienced by patients:
- Runny nose
- Minor pain
- Crusting
- Little blood discharge
When necessary, the ENT surgeon may clean the nose and check healing during follow-up visits.
Rather than guaranteeing that every patient would recover within a set number of days, the actual return-to-work or return-to-normal-activity schedule should be tailored to each individual.
Typical recovery milestones (based on NHS and ENT UK patient leaflets):
- First week: Nasal blockage, light bleeding and crusting are normal. Avoid blowing the nose forcefully, heavy lifting, strenuous exercise and air travel. Sleep with the head slightly elevated.
- Weeks 1–2: Begin regular saline rinses (as advised by your surgeon) to clear crusts and promote healing. Avoid alcohol for roughly two weeks (it thins the blood). Return to light work is usually possible after 1–2 weeks.
- Weeks 2–6: Gradual improvement in nasal breathing and smell. Follow-up endoscopy may be done to clean the sinus cavity. International evidence-based guidelines now recommend saline-based nasal irrigations after endoscopic sinus surgery, and in selected patients, steroid-containing irrigations, to speed mucosal recovery and reduce recurrence.
- 6–8 weeks: Most patients are fully back to normal activities and sports. Final healing of the sinus lining can continue quietly for 3–6 months.
If severe pain, high fever, visual changes, heavy bleeding, or clear watery fluid from the nose develop at any point after surgery, the operating ENT team should be contacted urgently.
16. Is it possible for a sinus cyst to disappear on its own?
Indeed, some maxillary sinus retention cysts may spontaneously diminish or vanish.
According to long-term follow-up investigations, a large number of retention cysts either vanished, shrunk in size, or remained stable, while only a small number grew in size.
According to a literature study, around:
- The size decreased by 30%.
- 50–60% of them remained the same.
- increased by 8 to 20 percent
Depending on how the cysts are identified and monitored, the precise percentages change from one research to another.
Because of this, an asymptomatic, incidental cyst does not typically need surgery.
Why do cysts resolve? Spontaneous resolution is thought to happen when the duct that was blocked re-opens, letting the trapped mucus drain back into the sinus. Treating any contributing allergy, infection or mucosal inflammation may help this process along. Because so many cysts shrink or stay stable, specialist bodies now recommend a conservative “watch and rescan” approach, typically with a follow-up scan after 6–12 months rather than immediate intervention — especially in people without symptoms.
17. Is It Possible for Sinus Cysts to Reappear?
Recurrence or the formation of another retention cyst can occur if a retention cyst is surgically treated.
Recurrence, however, must be understood in light of the patient’s underlying sinus disorder.
Even after a specific cyst is treated, symptoms may persist if persistent inflammation, allergies, dental disease, or poor sinus drainage are present.
Factors that increase recurrence risk include: uncontrolled allergic rhinitis, untreated chronic rhinosinusitis, ongoing cigarette smoking, continued exposure to irritants or occupational dust, and underlying dental disease that was never addressed. Mucoceles, in particular, have a non-trivial recurrence rate — reported anywhere between a few percent and up to 25% depending on the sinus involved and the completeness of the original surgery — which is why long-term follow-up with repeat endoscopy or imaging is routine after mucocele surgery.
18. Preventing Sinus Issues in the Future
There is no surefire way to avoid every retention cyst.
General actions that can encourage sinus health include:
- Controlling allergic rhinitis
- Avoiding cigarette smoke.
- Keeping your teeth clean
- Proper sinus infection treatment
- After the recommended nasal therapies
- Maintaining appropriate fluid balance
- Looking for an assessment of persistent one-sided sinus symptoms
➕ Extra prevention tips supported by WHO, CDC and NHS guidance:
- Vaccination — annual influenza vaccination (and age-appropriate pneumococcal, COVID-19 and other recommended vaccines) reduces upper respiratory infections that can trigger sinus inflammation.
- Hand hygiene and respiratory etiquette — simple handwashing with soap and water is one of the most effective ways to reduce viral upper respiratory infections (WHO/CDC).
- Humidify indoor air during dry seasons; keep humidifiers scrupulously clean to avoid mould growth.
- Avoid prolonged use of OTC decongestant sprays (rebound congestion risk after 3–5 days).
- Timely dental checks — treating decayed upper teeth and periodontal disease early reduces the risk of odontogenic sinus disease.
- Protect against air pollution — wearing a well-fitting mask on high-pollution days or in dusty workplaces can reduce mucosal irritation.
- Manage reflux — laryngopharyngeal reflux can worsen sinonasal inflammation; weight management, late-meal avoidance and medical treatment where appropriate can help.
19. When Should I Consult an ENT Specialist?
See an ENT expert if you have:
- Pain or constant pressure in the face
- Ongoing blockage of the nasal passages
- Recurrent sinus infection
- Postnasal drainage that continues
- Feeling of smell is reduced.
- Unilateral sinus symptoms that do not go away
- Upper tooth or cheek pain that keeps returning
- Symptoms that persist despite proper treatment
- An abnormal finding on a sinus CT or MRI that has not been elucidated
Do not believe that all of your symptoms are caused by every abnormality seen on a CT scan.
🚑 Seek urgent / same-day medical attention if you develop:
- Severe one-sided facial swelling or redness
- Swelling around the eye, double vision, loss of vision or bulging eye
- Severe headache with neck stiffness, confusion or high fever
- Bleeding from the nose that will not stop
- Clear watery fluid dripping from the nose after any sinus or facial trauma or surgery
These may signal complications (orbital or intracranial spread of infection, mucocele pressing on neighbouring structures, or CSF leak) that require immediate ENT assessment.
20. FAQs
Are sinus cysts harmful?
Especially when they are small and symptomless, most retention cysts in the maxillary sinus are benign and harmless.
Is there a chance that a sinus cyst could turn cancerous?
A retention cyst in the maxillary sinus is usually benign. Nevertheless, a rare cystic lesion should be carefully examined before being automatically presumed to be a retention cyst.
Is it possible for a sinus cyst to go away on its own without requiring surgery?
Yes, that’s right. Some retention cysts spontaneously disappear or reduce in size.
Does every cyst require surgery?
No. The majority of asymptomatic retention cysts do not need to be surgically removed.
Is it possible for a sinus cyst to cause headaches?
A cyst on a CT scan does not automatically indicate that it is the cause of a headache, even if the headache is accompanied by facial pressure.
Does tooth discomfort caused by a sinus cyst occur?
Cheek or upper jaw symptoms may be caused by a lesion in the maxillary sinus, but they can also be caused or exacerbated by tooth illness. So, a dental exam might be required.
Are nasal polyps and sinus cysts the same thing?
No. Because they are different forms of lesions and have distinct looks and treatment options, a nasal polyp and a retention cyst are different.
Which scan is ideal for a sinus cyst?
The paranasal sinuses and their nearby anatomy are frequently examined using CT. MRI may be used selectively when additional soft-tissue characterization is necessary.
Is it possible for sinus cysts to expand?
Others shrink, and a small number increase in size, while others stay constant.
Does a large cyst always require endoscopic surgery?
No. Treatment shouldn’t be based solely on size, but rather on the whole clinical picture, which includes symptoms, blockage, concurrent conditions, and imaging findings.
How often should an incidentally found sinus cyst be re-scanned?
There is no universal rule, but most ENT specialists favour a follow-up scan at 6–12 months for an asymptomatic cyst, then less frequently if the cyst is stable or shrinking. More rapid follow-up is justified if the lesion appears unusual, is one-sided and large, or if new symptoms develop.
Can a sinus cyst affect flying or scuba diving?
In most cases, small asymptomatic retention cysts do not cause problems with changes in cabin or water pressure. However, if the cyst is blocking a sinus outlet, pressure changes can trigger significant facial pain (barotrauma). Anyone with ongoing sinus symptoms planning long-haul flights or diving should discuss this with their ENT specialist in advance.
Can children have sinus cysts?
Yes. Although less commonly reported than in adults, maxillary retention cysts and mucoceles do occur in children and adolescents. Because children’s sinuses are still developing, any suspicious lesion should be evaluated by a paediatric ENT specialist.
Is a sinus cyst related to COVID-19 or long COVID?
There is no evidence that COVID-19 directly causes retention cysts. However, severe or repeated viral upper respiratory infections can contribute to chronic mucosal inflammation, which in turn is one of the recognised risk factors for cyst formation.
21. Key Takeaways
- Generally harmless, retention cysts in the maxillary sinus.
- Many are found by coincidence and don’t manifest any symptoms.
- A headache or facial discomfort does not necessarily indicate that the cyst is the cause.
- Some cysts can go away on their own or decrease in size.
- Particularly when unilateral maxillary sinus disease is present, dental disease should be taken into account.
- The diagnosis can be established with nasal endoscopy and CT.
- Surgery is not usually needed for asymptomatic, incidental cysts.
- For select obstructive or symptomatic cases, endoscopic surgery may be a viable choice.
- Findings from an unusual or unexplained unilateral sinus should be examined by a specialist.
- Up to 30–50% of maxillary sinusitis — and up to 75% of one-sided maxillary sinusitis — is of dental origin, so a dental review matters.
- Saline nasal irrigation plus intranasal corticosteroid is the guideline-recommended first-line medical treatment for ongoing sinus symptoms.
- Mucoceles, unlike simple retention cysts, almost always need surgery because they can expand and press on the eye or brain.
22. Conclusion
Typically benign and common, a retention cyst of the maxillary sinus is. Many patients have no symptoms and never require treatment.
The crucial question when symptoms like facial pressure, headache, nasal obstruction, recurrent sinus problems, or discomfort in the upper jaw appear is not just whether a cyst exists, but whether the cyst is actually to blame for the symptoms.
Similar complaints might be brought on by other medical conditions such as migraine, dental disease, nasal inflammation, and chronic rhinosinusitis.
An underlying cause can be determined and needless treatment can be avoided with a thorough ENT evaluation, suitable imaging, nasal endoscopy, and dental evaluation if needed.
In patients with symptoms, endoscopic therapy may be taken into consideration if the cyst or accompanying sinus condition is clinically important. Observation, however, is completely acceptable for a number of incidental cysts.
The best outcomes come from a combined approach — accurate imaging (ideally CT or CBCT), honest symptom assessment, dental review when the disease is one-sided, evidence-based medical treatment (saline rinses, intranasal steroids, allergy control), and surgery only when it is clearly justified. If you are unsure about a scan report mentioning a sinus cyst, do not assume the worst and do not rush into treatment: a short consultation with an experienced ENT specialist can usually clarify whether the cyst matters at all for your particular symptoms.
📞 ENT Consultation
Dr. Sagar Rajkuwar, MS-ENT
Prabha ENT Clinic, Ambad, Nashik, Maharashtra, India
Phone: 7387590194 | 9892596635
Clinic website: ENT Specialist in Nashik
Medical Disclaimer
This article is intended for general health education and does not replace an in-person medical examination, diagnosis, or individualized treatment plan.
Do not start, stop, or change medication or decide to undergo surgery based solely on information found online. If you have persistent, severe, or worsening symptoms, consult a qualified ENT specialist.
📲 For Health-Related Articles & Videos
🔹 Facebook: https://www.facebook.com/positivemind.healthcare
🔹 YouTube: http://www.youtube.com/@healthuseful8539/
Medical References
- Cysts of the Maxillary Sinus: A Literature Review. PubMed.
- Natural Course of Retention Cysts of the Maxillary Sinus: Long-Term Follow-Up Results. PubMed.
- Sinus Radiological Findings in General Asymptomatic Populations. PubMed.
- Unilateral Sinus Disease: What Is, and Is Not Odontogenic Sinusitis? PubMed.
- Definition and Management of Odontogenic Maxillary Sinusitis. PubMed.
- Symptomatic Maxillary Sinus Retention Cysts: Should They Be Removed? PubMed.
- Frequency of Maxillary Sinus Mucous Retention Cysts in a Central Brazilian Population. J Dent (Shiraz), 2015.
- Diagnosis and Management of Maxillary Sinusitis of Endodontic Origin. CDE World / American Association of Endodontists position statement.
- International Consensus Statement on Allergy and Rhinology: Rhinosinusitis (ICAR-RS). American Academy of Otolaryngology–Head and Neck Surgery.
- Saline nasal irrigation for chronic rhinosinusitis. NIHR Evidence summary of UK primary-care RCT and Cochrane review.
- NICE Clinical Knowledge Summary — Sinusitis (acute and chronic). National Institute for Health and Care Excellence, UK.
- Advice following nasal surgery (FESS). Royal Berkshire NHS Foundation Trust / East and North Hertfordshire NHS Trust patient leaflets.
- Sinonasal mucocele overview. Penn Medicine; EyeWiki (American Academy of Ophthalmology).
- Common Cold and Sinusitis prevention. U.S. Centers for Disease Control and Prevention (CDC).
- Tobacco use and respiratory disease fact sheets. World Health Organization (WHO).
🔗 Sinus Related Articles (Internal Links)
🤧 Sinus Headache & Symptoms
- https://healthuseful.com/sinus-headache-symptoms/
- https://healthuseful.com/sinus-headache-symptoms-one-side/
- https://healthuseful.com/sinus-headache-symptoms-right-side/
- https://healthuseful.com/sinus-headache-back-of-head/
- https://healthuseful.com/sinus-headache-symptoms-home-remedies/
- https://healthuseful.com/how-to-rid-of-a-sinus-infection-headache/
🦠 Sinus Infection Treatment
- https://healthuseful.com/how-to-get-rid-of-a-sinus-infection-in-24-hours/
- https://healthuseful.com/how-to-get-rid-of-sinus-infection-without-antibiotics/
- https://healthuseful.com/what-kills-a-sinus-infection-naturally/
- https://healthuseful.com/sinus-headache-tablet/
- https://healthuseful.com/how-do-doctors-drain-sinuses-without-surgery/
- https://healthuseful.com/signs-of-sinus-infection-getting-better/
- https://healthuseful.com/signs-of-sinus-infection-getting-better-with-antibiotics/
⚠️ Serious Conditions & Warning Signs
- https://healthuseful.com/end-stages-of-a-sinus-infection/
- https://healthuseful.com/how-to-tell-if-sinus-infection-has-spread-to-brain/
- https://healthuseful.com/how-to-tell-if-sinus-infection-has-spread-to-bone/
- https://healthuseful.com/what-is-a-red-flag-for-sinusitis/
- https://healthuseful.com/when-to-go-to-ae-with-sinusitis/
👁️ Related Symptoms & Complications
- https://healthuseful.com/can-a-sinus-infection-cause-eye-pain/
- https://healthuseful.com/can-sinusitis-affect-your-ears/
- https://healthuseful.com/can-sinus-infection-cause-hair-loss/
- https://healthuseful.com/symptoms-of-perforated-sinus-after-tooth-extraction/
🧠 Causes, Triggers & Misdiagnosis
- https://healthuseful.com/what-triggers-sinusitis-headaches/
- https://healthuseful.com/what-can-be-mistaken-for-a-sinus-infection/
- https://healthuseful.com/what-mimics-sinus-issues/
- https://healthuseful.com/what-can-worsen-a-sinus-infection/
🧬 Nutrition & Deficiency
- https://healthuseful.com/what-vitamin-deficiency-causes-sinus-headaches/
- https://healthuseful.com/what-vitamin-deficiency-causes-sinusitis/
- https://healthuseful.com/what-deficiency-causes-sinusitis/
📘 General Sinus Knowledge
- https://healthuseful.com/what-are-the-four-cardinal-signs-of-sinusitis/
- https://healthuseful.com/is-a-sinus-infection-contagious-with-fever/
- https://healthuseful.com/can-you-smell-a-fungal-sinus-infection/
- https://healthuseful.com/sinusitis-in-hindi/
💰 Treatment & Surgery
- https://healthuseful.com/cost-of-sinus-surgery-in-india/
- https://healthuseful.com/how-to-cure-sinus-permanently/
🧒 Special Cases
🔍 Rare Conditions
🔗 Related Articles on Nasal Polyps (ENT Expert Guides)
For detailed, evidence-based information, explore the following articles:
https://healthuseful.com/can-nasal-polyps-turn-cancerous/
https://healthuseful.com/can-nasal-polyps-affect-the-brain/
https://healthuseful.com/what-are-the-symptoms-of-cancerous-nasal-polyps/
https://healthuseful.com/when-to-worry-about-nasal-polyp/
https://healthuseful.com/what-happens-if-nasal-polyps-untreated/
https://healthuseful.com/number-one-cause-of-nasal-polyps/
https://healthuseful.com/how-to-stop-polyp-growth/
https://healthuseful.com/can-nasal-polyps-cause-heart-problems/
https://healthuseful.com/how-to-cure-nasal-polyps-permanently/
https://healthuseful.com/can-ent-see-nasal-polyps/