How Do You Confirm Gastroenteritis? Diagnosis, Tests and When to Seek Medical Help-various aspects
Article author: Dr. Sagar Rajkuwar, MS-ENT
🌐 www.entspecialistinnashik.com
Introduction
Sudden diarrhoea, vomiting, nausea and abdominal cramps commonly suggest gastroenteritis, an inflammation of the stomach and intestines. But how do you confirm gastroenteritis, and is a stool test always necessary? Many people assume that a blood test or stool examination is required in every case. In reality, doctors can often make a working diagnosis from the symptoms, exposure history and physical examination. Laboratory investigations are reserved for selected situations, such as bloody diarrhoea, severe illness, prolonged symptoms, suspected outbreaks or a weakened immune system. This guide explains the diagnostic process step by step, what different tests can and cannot establish, how doctors assess dehydration, and which symptoms may indicate a more serious condition.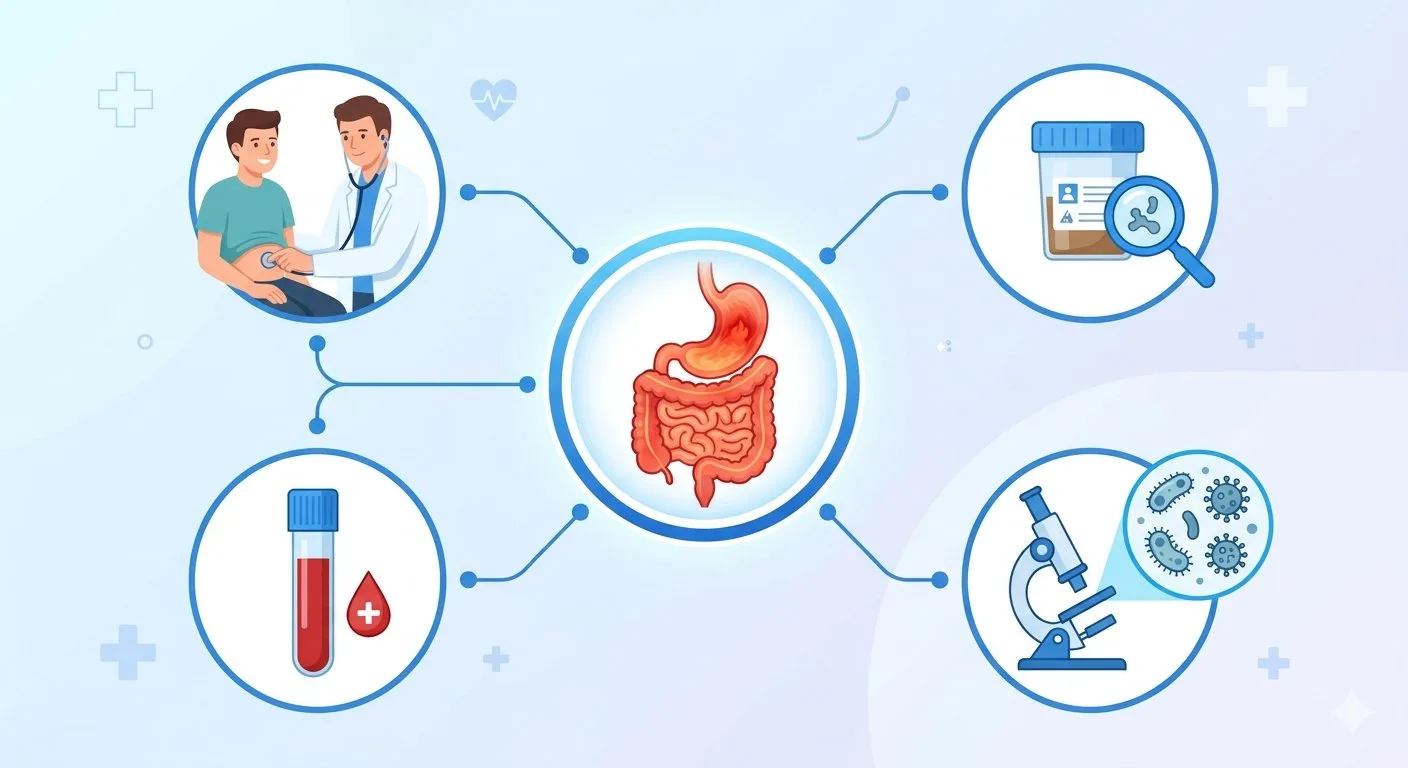
How Do You Confirm Gastroenteritis?
Direct answer: Gastroenteritis is usually confirmed clinically by reviewing the onset and pattern of diarrhoea or vomiting, associated symptoms, possible food or water exposure, contact with infected people, travel and a physical examination. A stool test may identify a bacterial, viral or parasitic cause when testing is indicated. Blood tests are generally used to assess dehydration, electrolyte disturbances, kidney function or complications rather than to confirm uncomplicated gastroenteritis itself.
There is no single routine test that every patient needs. The doctor first decides whether the overall presentation fits acute gastroenteritis and whether another diagnosis must be considered. Therefore, the answer to “how do you confirm gastroenteritis?” depends on the patient’s age, severity, duration, medical history and warning signs.
1. What Does Gastroenteritis Mean?
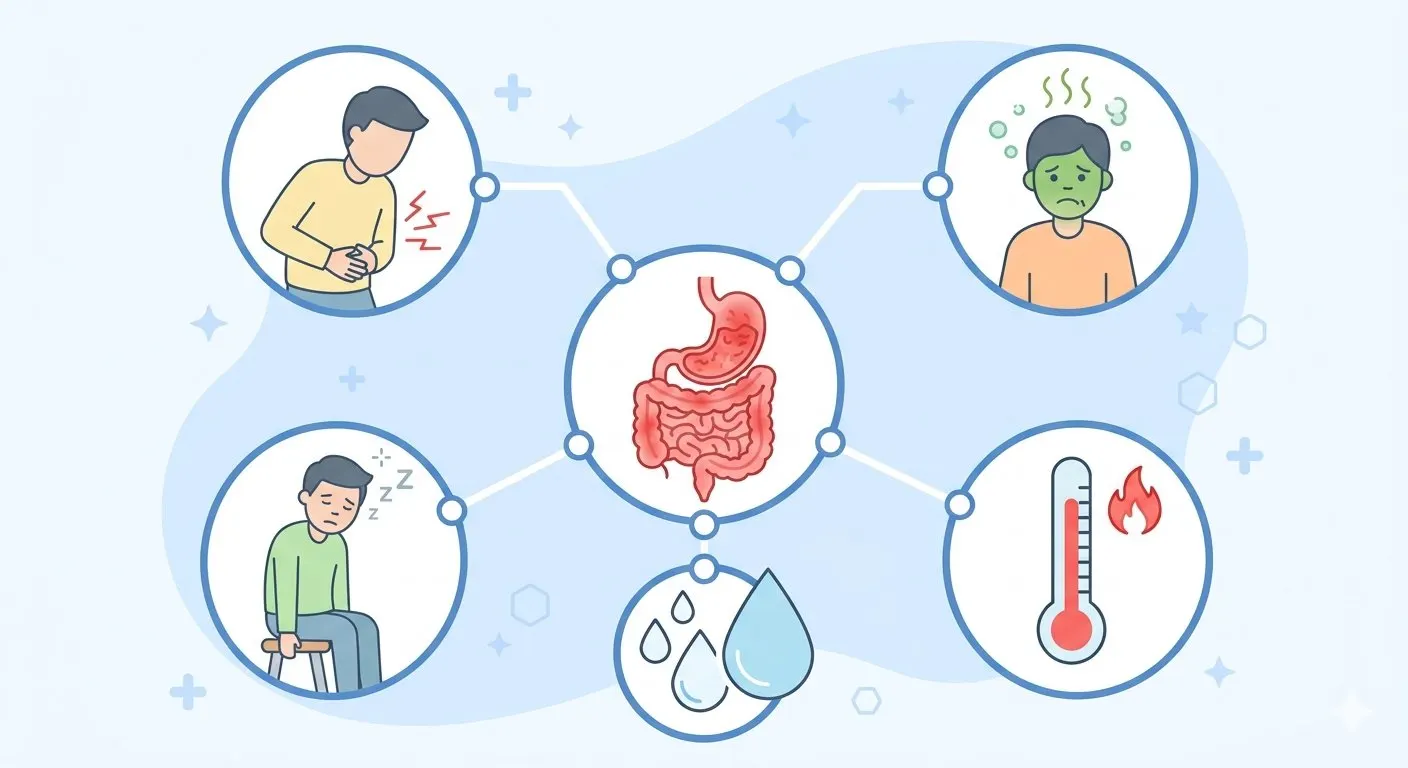
Gastroenteritis is inflammation of the gastrointestinal tract, particularly the stomach and intestines. It commonly causes sudden-onset loose or watery stools, vomiting, nausea, abdominal cramps and sometimes fever. Infectious gastroenteritis may be caused by viruses, bacteria or parasites. Foodborne toxins and certain non-infectious conditions can produce a similar illness. The World Health Organization defines diarrhoea as passing three or more loose or liquid stools per day, or more frequently than is normal for that individual. Stool frequency alone is not enough to identify the cause. A person may have diarrhoea due to medication, inflammatory bowel disease or another condition without having infectious gastroenteritis.Common symptoms doctors look for
- Sudden onset of loose or watery stools.
- Nausea and one or more episodes of vomiting.
- Cramp-like abdominal discomfort.
- Fever, chills, headache or body aches in some infections.
- Reduced appetite and weakness.
- Signs of fluid loss, such as thirst, dry mouth, dizziness or reduced urination.
2. Step 1: Medical History – The First Part of Diagnosis
A careful history often provides the most useful initial clues. When considering how do you confirm gastroenteritis, clinicians begin by understanding exactly what happened and how the illness has progressed.Questions a doctor may ask
- Onset: When did diarrhoea or vomiting begin? Was the onset sudden or gradual?
- Frequency: How many loose stools or vomiting episodes have occurred in 24 hours?
- Stool appearance: Is it watery, bloody, black, greasy or associated with mucus?
- Associated symptoms: Is there fever, abdominal pain, tenesmus, bloating or reduced urine output?
- Food and water exposure: Was there recently undercooked food, unpasteurised food, unsafe drinking water or a shared meal followed by illness in others?
- Contact history: Has anyone at home, school, workplace or a healthcare facility had similar symptoms?
- Travel: Has the patient recently travelled, especially to an area with different food or water safety conditions?
- Medication: Has the patient recently taken antibiotics, laxatives, antacids containing magnesium or other medicines that can cause diarrhoea?
- Medical background: Is there pregnancy, diabetes, kidney disease, inflammatory bowel disease, cancer treatment or immune suppression?
Why timing and exposure matter
Several people becoming ill after sharing a meal may suggest a common foodborne exposure. A cluster of vomiting and watery diarrhoea among family members or in a school, hostel or healthcare facility may suggest a contagious infection such as norovirus. Recent antibiotic use or hospitalisation raises concern for Clostridioides difficile, particularly when diarrhoea is significant. These clues help select appropriate tests; they do not prove a specific organism by themselves.3. Step 2: Physical Examination and Assessment of Dehydration
The physical examination helps the clinician judge severity and look for complications or alternative diagnoses. It is an essential part of deciding how do you confirm gastroenteritis safely, rather than relying on symptoms alone.Vital signs
- Temperature: Fever may occur with infection; a high fever can increase concern for invasive bacterial disease or another serious illness.
- Pulse: A fast pulse may occur with fever, pain or dehydration.
- Blood pressure: Low blood pressure, particularly with dizziness or collapse, may indicate significant fluid loss or shock.
- Respiratory rate and general appearance: Rapid breathing, confusion or severe weakness requires prompt assessment.
Examination for dehydration
Doctors assess thirst, alertness, mouth and tongue moisture, eye appearance, skin perfusion, capillary refill, urine history and circulation. No single sign is perfect; findings are interpreted together and in the context of age and medical conditions.| Finding | Why it matters |
|---|---|
| Dry mouth and intense thirst | May indicate fluid deficit. |
| Reduced or dark urine | Can reflect reduced fluid intake or fluid loss. |
| Dizziness on standing | May indicate reduced circulating volume. |
| Fast pulse, cold extremities or delayed capillary refill | Can suggest impaired circulation and more serious dehydration. |
| Lethargy, confusion or inability to drink | Concerning features requiring urgent medical assessment. |
Abdominal examination
The doctor checks for tenderness, guarding, rebound tenderness, distension and bowel sounds. Mild, diffuse cramping can occur in gastroenteritis. Severe pain in one area, a rigid abdomen or pain with guarding raises concern for conditions such as appendicitis, bowel obstruction, pancreatitis or other acute abdominal disorders.4. Step 3: Stool Tests – When Are They Needed?
A stool test is not routinely required in every person with a short-lived, mild episode of watery diarrhoea. If the clinical picture is typical and the patient is stable, testing may not change treatment. However, stool testing becomes more useful when the illness is severe, unusual, prolonged or potentially linked to an outbreak.Situations in which stool testing may be recommended
- Blood or mucus in stool: may indicate inflammatory or invasive infection and requires assessment.
- High fever or severe abdominal cramps/tenderness: can justify testing for important bacterial pathogens.
- Severe or persistent diarrhoea: particularly when symptoms are not improving or last longer than expected.
- Immunocompromised patients: the range of possible pathogens and risk of complications is broader.
- Recent travel: especially if symptoms persist or a specific exposure is suspected.
- Recent antibiotics or hospital care: consider testing for C. difficile when clinically appropriate.
- Suspected outbreak: testing selected patients can help public health teams identify the source and organism.
Types of stool investigations
| Test | What it can detect or assess | When it may be useful |
|---|---|---|
| Stool culture | Growth of selected bacteria such as Salmonella, Shigella and Campylobacter, depending on laboratory methods. | Suspected bacterial diarrhoea, selected severe cases and public health investigations. |
| Multiplex PCR / gastrointestinal pathogen panel | Genetic material from several bacteria, viruses and parasites in one sample, depending on the panel. | Selected moderate-to-severe, persistent or diagnostically unclear cases. |
| Parasite antigen or molecular tests | Organisms such as Giardia or Cryptosporidium, depending on the assay. | Persistent diarrhoea, relevant water/travel exposure or specific clinical suspicion. |
| Ova and parasite microscopy | Parasite eggs, cysts or organisms, depending on sample quality and laboratory expertise. | Selected prolonged illness or suspected parasitic infection. |
| C. difficile toxin/NAAT testing | Evidence of toxigenic C. difficile in an appropriate symptomatic patient. | Clinically significant diarrhoea after antibiotics or healthcare exposure, according to local criteria. |
| Stool occult blood or inflammatory markers | May provide evidence of blood or intestinal inflammation but do not identify the organism. | Selected situations; not a universal confirmation test. |
How should a stool sample be collected?
- Use the clean, leak-proof container supplied or recommended by the laboratory.
- Avoid mixing the sample with urine, toilet water or cleaning products.
- Collect a representative portion of fresh diarrhoeal stool as instructed.
- Close and label the container correctly and deliver it within the laboratory’s specified time.
- Follow the laboratory’s instructions for refrigeration, transport medium and storage; requirements vary by test.
Important: A negative stool test does not exclude every infection. The result depends on the organism included in the test, timing, sample quality, prior treatment and test sensitivity. A positive molecular test also needs clinical interpretation because detection of genetic material does not always prove that the detected organism is causing the current symptoms.
5. Step 4: Blood Tests and Other Investigations
Blood tests do not usually establish uncomplicated gastroenteritis or identify its infectious cause. They are used when the patient’s condition suggests dehydration, systemic illness, complications or another diagnosis.Common blood investigations
- Complete blood count (CBC): may show raised white blood cells or haemoconcentration, but these findings are non-specific and cannot reliably distinguish viral from bacterial gastroenteritis.
- Electrolytes: sodium, potassium, chloride and bicarbonate can help identify disturbances caused by vomiting and diarrhoea.
- Urea and creatinine: help assess kidney function and possible effects of dehydration.
- Blood glucose: particularly relevant in people with diabetes, children who are unwell, or patients with altered consciousness.
- CRP and other inflammatory markers: may support assessment of inflammation but cannot confirm a particular pathogen.
- Blood cultures: may be required if sepsis, enteric fever or bloodstream infection is suspected, ideally before antibiotics when this does not delay urgent treatment.
When imaging may be required
Ultrasound or CT scanning is not a routine test for straightforward gastroenteritis. Imaging may be appropriate when examination findings suggest appendicitis, bowel obstruction, perforation, pancreatitis, gallbladder disease or another abdominal condition. The choice depends on the suspected diagnosis, age, pregnancy status and clinical urgency.6. How Do Doctors Identify the Organism Causing Gastroenteritis?
Symptoms can overlap substantially, so the exact cause cannot always be identified from appearance alone. A clinician combines exposure history, symptom pattern, examination and, when justified, laboratory results.| Possible cause | Typical clues (not diagnostic on their own) | Possible test when indicated |
|---|---|---|
| Norovirus | Sudden vomiting and watery diarrhoea; outbreaks in families, schools, institutions or cruise settings. | Stool RT-PCR, particularly in outbreak investigations or selected cases. |
| Rotavirus | Important cause of acute diarrhoea in young children, especially where vaccination coverage is incomplete. | Stool antigen or molecular assay when testing is needed. |
| Salmonella | Diarrhoea, fever and abdominal cramps; possible exposure to contaminated food. | Stool culture or molecular testing. |
| Shigella | Fever, cramps, urgency and sometimes bloody diarrhoea. | Stool culture or molecular testing. |
| Campylobacter | Fever and abdominal pain with diarrhoea, sometimes bloody; food exposure may be relevant. | Stool culture or molecular testing. |
| Giardia | Prolonged diarrhoea, bloating and sometimes greasy or foul-smelling stools; untreated water exposure may be relevant. | Stool antigen or molecular testing; microscopy in selected cases. |
| Entamoeba histolytica | May cause dysentery or prolonged intestinal symptoms, depending on exposure and disease. | Specific stool antigen or molecular testing; microscopy alone may not reliably distinguish species. |
Why norovirus is a useful example
Norovirus is often diagnosed from a typical clinical picture, particularly during a recognised outbreak. Testing is not routinely needed to guide care for every individual. When laboratory confirmation is important, RT-qPCR on a whole stool specimen is a preferred method. A rapid antigen test may be less sensitive and is not a substitute for molecular testing in outbreak investigations.7. Conditions That Can Mimic Gastroenteritis
Not every episode of diarrhoea and abdominal pain is gastroenteritis. A clinician should consider alternative causes when the pattern is atypical, pain is severe or localised, symptoms persist, or examination findings are concerning.Important alternative diagnoses
- Appendicitis: pain may become localised to the right lower abdomen; vomiting and sometimes diarrhoea can occur.
- Inflammatory bowel disease: recurrent or persistent diarrhoea, blood in stool, weight loss or extra-intestinal symptoms may be present.
- Medication-related diarrhoea: antibiotics, metformin, magnesium-containing products and laxatives are examples of possible contributors.
- Food intolerance: symptoms may repeatedly follow a particular food rather than a sudden infectious exposure.
- Pancreatitis or gallbladder disease: may cause significant upper abdominal pain and vomiting.
- Bowel obstruction: distension, vomiting and inability to pass stool or gas are concerning features.
- Urinary infection or other abdominal/pelvic conditions: can produce overlapping symptoms.
8. Warning Signs: When Should You Seek Medical Help?
Seek urgent medical assessment if there is blood in the stool or vomit, severe or localised abdominal pain, confusion, fainting, very little or no urine, inability to keep fluids down, signs of shock, or rapidly worsening illness.
Warning signs of dehydration
- Marked thirst, dry mouth or sunken eyes.
- Passing much less urine than usual or no urine for an unusually long period.
- Dizziness, fainting, unusual drowsiness or confusion.
- Fast heartbeat, cold hands and feet, or severe weakness.
- In children: fewer wet nappies, poor feeding, reduced activity or unusual sleepiness.
People who may need earlier assessment
Infants and young children, older adults, pregnant people, people with kidney or heart disease, diabetes, significant chronic illness or weakened immunity may deteriorate more quickly. They should seek advice early if diarrhoea or vomiting is substantial or fluid intake is poor.9. How Is Gastroenteritis Confirmed in Children and Older Adults?
Children
In children, diagnosis is usually clinical. The doctor asks about stool frequency, vomiting, feeding, fluid intake, urine or wet nappies, fever, contacts and travel. The examination focuses on hydration, alertness, circulation and abdominal findings. Stool testing is considered for blood or mucus, suspected sepsis, immune compromise, travel, diagnostic uncertainty or diarrhoea that is not improving within the expected period. Green (bilious) vomiting, severe or localised abdominal pain, abdominal distension, altered consciousness, breathing difficulty or a non-blanching rash should prompt urgent assessment rather than being assumed to be routine gastroenteritis.Older adults
Older adults may have a higher risk of dehydration and complications, particularly if they take diuretics or medicines affecting kidney function, or have limited ability to drink independently. A clinician may have a lower threshold for checking electrolytes and kidney function when fluid loss is significant or the patient appears unwell.10. What Should You Do While Waiting for Test Results?
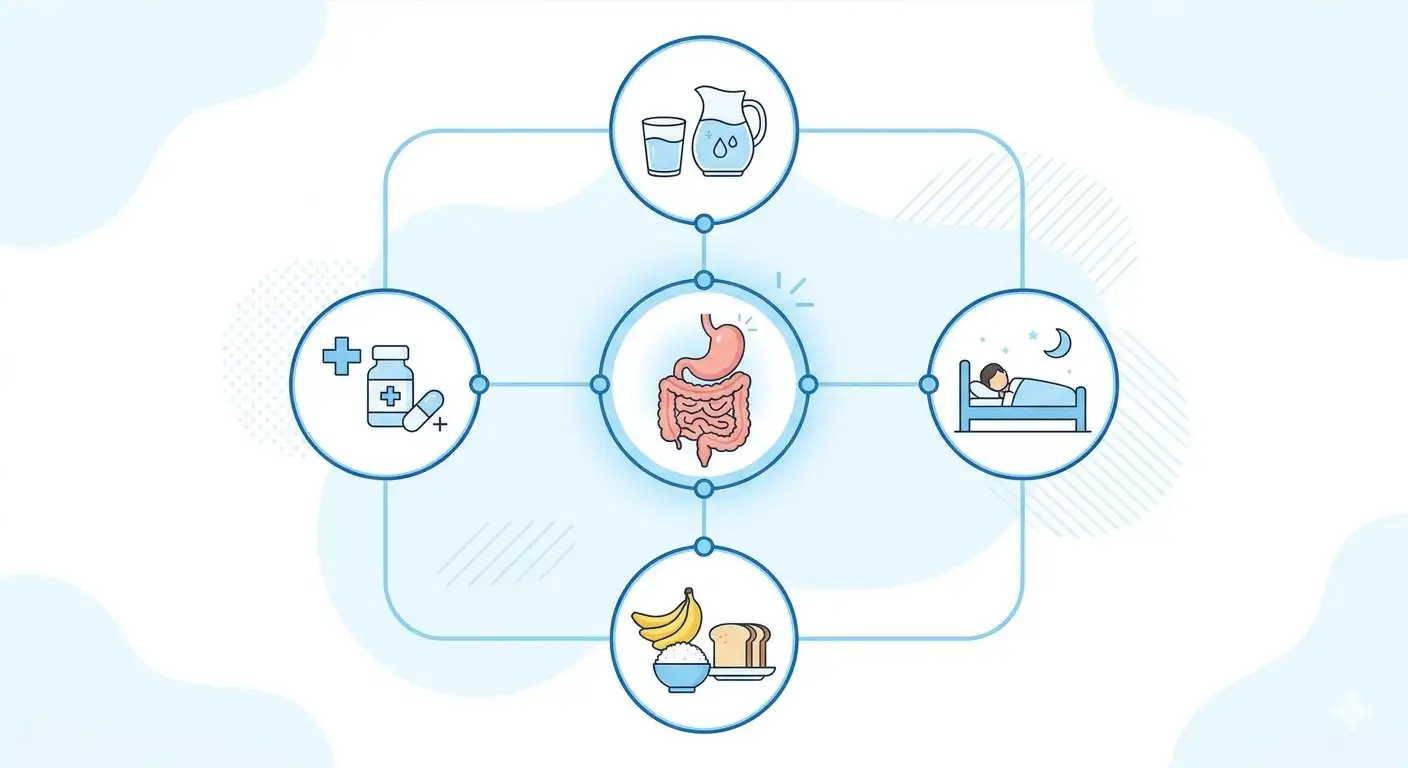
For most uncomplicated acute diarrhoeal illnesses, the immediate priority is preventing or correcting dehydration. Treatment should not be delayed while waiting for a stool result if the patient needs fluid replacement or urgent care.Practical steps
- Use oral rehydration solution (ORS): prepare it exactly as directed on the packet, using the stated volume of safe water. Offer frequent small sips, especially after vomiting or loose stools.
- Continue appropriate food: resume or continue normal age-appropriate food as tolerated. Breastfeeding should continue in infants.
- Avoid unsafe self-medication: antibiotics do not treat viral gastroenteritis and are not appropriate for every bacterial diarrhoea. Some infections require specific treatment, while others may be harmed by inappropriate antibiotics.
- Be cautious with anti-diarrhoeal medicines: they are not suitable for everyone, particularly children or people with fever or bloody diarrhoea. Ask a clinician or pharmacist before use.
- Prevent spread: wash hands with soap and water, clean contaminated surfaces safely, avoid preparing food for others while ill, and follow local infection-control advice.
When should symptoms improve?
The course varies with the cause. Many short-lived viral illnesses improve over a few days, but diarrhoea can last longer. Persistent, worsening or recurrent symptoms require reassessment rather than repeated self-treatment.11. A Quick Diagnostic Pathway: From Symptoms to Diagnosis
Sudden vomiting and/or diarrhoea ↓ 1. Take a focused history Onset, duration, stool features, fever, food/water exposure, travel, sick contacts, medicines and medical risks. ↓ 2. Examine the patient Vital signs, hydration, circulation and abdominal examination. ↓ 3. Decide whether the presentation is uncomplicated • Mild, short-lived illness; stable patient; no red flags → clinical diagnosis may be sufficient; routine tests often unnecessary. • Blood/mucus, fever with severe symptoms, persistent illness, immune compromise, recent antibiotics/hospitalisation or outbreak → consider targeted stool tests. • Significant dehydration or systemic illness → consider electrolytes, kidney function, glucose and other tests guided by the examination. ↓ 4. Reassess and interpret results in context A test result supports the diagnosis; it does not replace clinical judgement or assessment for alternative causes.
12. Key Takeaways
- Gastroenteritis is usually diagnosed from the history and physical examination.
- A stool test is not necessary for every mild, short-lived episode.
- Stool culture or molecular testing may be appropriate for bloody, severe, persistent or otherwise high-risk diarrhoea and outbreak investigations.
- Blood tests mainly assess dehydration, electrolyte imbalance, kidney function or complications; they do not usually identify the organism.
- Severe or localised abdominal pain, blood in stool, confusion, fainting or inability to drink needs prompt medical assessment.
- Oral rehydration and continued nutrition are central to supportive care, while antibiotics should be used only when clinically indicated.
13. Frequently Asked Questions (FAQs)
1. How do you confirm gastroenteritis?
Doctors usually diagnose it clinically by assessing the sudden onset of diarrhoea or vomiting, associated symptoms, exposure history and physical examination. Stool tests are used when the illness is severe, bloody, persistent, unusual or linked to an outbreak.2. Can gastroenteritis be diagnosed without a stool test?
Yes. Many mild, short-lived cases can be diagnosed from the clinical history and examination. Testing is not routinely required when the result is unlikely to change management.3. Which stool test confirms gastroenteritis?
There is no single test for every cause. Depending on the suspected organism, clinicians may request stool culture, multiplex PCR, pathogen-specific antigen testing, parasite testing or C. difficile testing. The choice should match the clinical situation.4. Can a CBC confirm gastroenteritis?
No. A CBC may show changes such as an increased white blood cell count, but these findings are non-specific. A CBC cannot reliably confirm gastroenteritis or distinguish viral from bacterial infection.5. Does a blood test show whether gastroenteritis is viral or bacterial?
Routine blood tests generally cannot reliably make this distinction. Stool microbiology may identify a pathogen when testing is indicated, but results must be interpreted alongside symptoms and examination findings.6. When should stool testing be done?
It may be recommended for bloody or mucoid diarrhoea, severe illness, significant fever or abdominal tenderness, persistent symptoms, immune compromise, recent travel, suspected C. difficile infection or an outbreak. Age-specific and local guidelines also matter.7. Can ultrasound or CT scan confirm gastroenteritis?
Imaging is not normally needed to diagnose uncomplicated gastroenteritis. It may be used when the doctor suspects another condition, such as appendicitis, obstruction or pancreatitis.8. How do doctors confirm viral gastroenteritis?
Often through the clinical pattern and exposure history. If laboratory confirmation is important, a stool molecular test such as RT-PCR may detect a virus such as norovirus. Testing is particularly useful in selected cases and outbreak investigations.9. How long can gastroenteritis last?
Duration depends on the cause and the individual. Many viral illnesses improve within a few days, but some infections last longer. Symptoms that persist, worsen or include warning signs should be medically reviewed.10. Is blood in the stool normal in gastroenteritis?
Blood is not a feature to dismiss as routine. It can occur with certain infections but may also indicate another intestinal condition. Medical assessment is recommended, particularly if there is fever, severe pain or dehydration.11. Can antibiotics confirm or cure gastroenteritis?
No. Antibiotics are treatments, not diagnostic tests, and they do not work against viruses. They are prescribed only for selected bacterial or parasitic causes when the expected benefit outweighs the risks.12. What is the most important thing to assess first?
Assess the patient’s overall condition and hydration. Severe dehydration, shock, altered consciousness or inability to keep fluids down requires urgent care, regardless of whether the exact organism has been identified.14. Helpful Video Resource
For additional patient education, see the WHO-related educational video search on diarrhoea and oral rehydration. Choose a video from a recognised health organisation or qualified healthcare professional. A video is supplementary and does not replace individual medical advice.15. Medical References and Further Reading
- National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK): Diagnosis of Viral Gastroenteritis.
- Infectious Diseases Society of America (IDSA): Clinical Practice Guidelines for the Diagnosis and Management of Infectious Diarrhea.
- World Health Organization (WHO): Diarrhoeal Disease Fact Sheet.
- US Centers for Disease Control and Prevention (CDC): Norovirus – Yellow Book.
- CDC: Laboratory Testing for Norovirus.
- National Institute for Health and Care Excellence (NICE): Diarrhoea and Vomiting Caused by Gastroenteritis in Under 5s – Diagnosis and Management.
- American College of Gastroenterology: Diagnosis, Treatment, and Prevention of Acute Diarrheal Infections in Adults.
- Chelsea and Westminster Hospital NHS Foundation Trust: Gastroenteritis – Patient Information.